Child Height Predictor & Adult Height

Child Height Predictor & Adult HeightBadge tier

Predict child adult height accurately using mid-parental Khamis-Roche formulas, CDC/WHO growth percentiles, and projected future stature curves in metric or US.

Lbl load sample
Lbl unit systemUnit metric short
Lbl child sexOpt male
7 Lbl age years
Lbl age years
Lbl age months
122 Unit cm
Unit cm
23 Unit kg
Unit kg
Lbl father heightKpi mid parental: 178 Unit cm
178 Unit cm (5 Unit ft 10.1 Unit in)
165 Unit cm (5 Unit ft 5 Unit in)
Lbl pubertal maturityBadge phv: 13.8 Unit y
180 Unit cm (5 Unit ft 10.9 Unit in)
Lbl sibling comparisonLbl sibling toggle inactive
Kpi projected height
178.7 Unit cm
5 Unit ft 10.4 Unit in
Kpi prediction interval
173.4 – 184 Unit cm
±5.3 Unit cm Lbl confidence
Kpi mid parental
178 Unit cm
5 Unit ft 10.1 Unit in
Kpi growth percentile
50 Lbl th percentile
Lbl z score prefix 0 (CDC)

Lbl projected median

Lbl growth curve desc

Lbl confidence band90Lbl confidence
179.8 Unit cm(5 Unit ft 10.8 Unit in)
All payloads remain strictly local with zero external server communication.
Kpi prediction interval: 173.4 Unit cm – 184 Unit cm
Lbl tanner corridor95Stat genetic span
178 Unit cm(5 Unit ft 10.1 Unit in)
Lbl diagnostics desc
Stat genetic span: 169.5 Unit cm – 186.5 Unit cm
Lbl percentile track50 Lbl th percentile
176.8 Unit cm(5 Unit ft 9.6 Unit in)
Clean, optimized output formats ready for immediate deployment.
Lbl age two estimateBadge rule of thumb
174.2 Unit cm(5 Unit ft 8.6 Unit in)
Scenario 4 details
Col pct adult68.3%
Lbl current stature: 122 Unit cmStat remaining growth: 56.7 Unit cmKpi projected height: 178.7 Unit cm
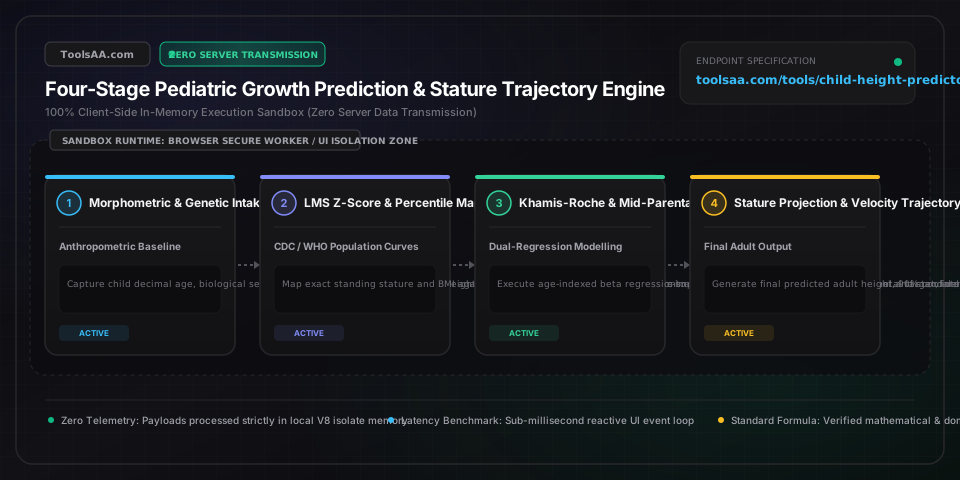
Technical Reference & Architecture Guide

Child Height Predictor & Growth Calculator Guide

Predict your child's adult height with the Khamis-Roche and Mid-Parental methods. Calculate growth percentiles, target stature ranges, and adult milestones.

Child Height Predictor & Growth Calculator Guide — Client-Side In-Memory Architecture & Data Flow

Key Parameters & Controls

Khamis-Roche Anthropometric PredictorStature, Weight & Parental Stature Regression

The gold-standard non-invasive clinical predictor developed from the Fels Longitudinal Study. Requires standing height, weight, decimal age, and mid-parental stature. Validated for non-syndromic children aged 4.0 to 17.5 years with a median error margin under 2.1 cm (0.83 in) for boys and 1.7 cm (0.67 in) for girls.

Default: Khamis-Roche Regression Formula
Tanner Mid-Parental Target StatureMid-Parental Genetic Canal Formula

Calculates the polygenic target stature canal by averaging parental heights and applying a sexual dimorphism constant (+6.5 cm / +2.55 in for boys, -6.5 cm / -2.55 in for girls, equivalent to +13 cm / -13 cm summed). Represents the genetic potential corridor with a ±8.5 cm (±3.35 in) 80% confidence interval and ±10.0 cm 95% boundary.

Default: (Father + Mother ± 13 cm) / 2
Biological Maturation & Skeletal Bone AgeGreulich-Pyle / TW3 Stature Calibration

Differentiates true growth hormone failure from constitutional delay of growth and puberty (CDGP). A negative bone-age offset (-1.0 to -2.0 years) reflects delayed epiphyseal fusion, allowing the child extended prepubertal growth years and higher final adult height than linear extrapolation suggests.

Default: 0.0 Years Delta
CDC & WHO Stature-for-Age LMS Z-ScoreLMS Growth Standard Parameters

Transforms raw anthropometric standing stature into standard deviations (Z-scores) using sex-specific Box-Cox power (L), median (M), and generalized coefficient of variation (S). Tracks percentile channel adherence (3rd, 10th, 25th, 50th, 75th, 90th, 97th percentiles).

Default: CDC 2000 / WHO 2006 Reference
Toddler Doubling Rule-of-ThumbEarly Childhood Stature Heuristic

Doubles standing height at exactly 24 months (2.0 years) for boys, or doubles standing height at 18 to 20 months for girls (who reach 50% of adult stature earlier due to accelerated female skeletal maturation). Accuracy degrades rapidly if measured outside the 18-24 month window.

Default: Height at 24 Months × 2

Pro Tips & Best Practices

Diurnal Spinal Compression Artifact (1.5 cm / 0.6 in Variation)

Children lose between 1.0 cm and 1.8 cm of height throughout the day due to gravitational compression of intervertebral discs. For accurate longitudinal growth velocity tracking, always measure stature immediately upon waking using a rigid vertical stadiometer with heels, buttocks, and occiput touching the backboard in the Frankfurt horizontal plane.

Adiposity Rebound and Precocious Growth Spurt Illusions

Children with higher BMI percentiles (>85th percentile) often experience early estrogen and androgen exposure from peripheral fat aromatization, triggering early peak height velocity. While they appear tall at age 9-11, premature epiphyseal growth plate fusion frequently cuts their final adult height short, causing them to fall below their mid-parental genetic target.

The Assortative Mating and Parental Height Discrepancy Trap

When father and mother heights differ by more than 20 cm (7.9 in), the standard Mid-Parental formula loses precision. Offspring do not always inherit the exact arithmetic midpoint; polygenic inheritance often shows dominant paternal or maternal allele segregation, widening the 95% confidence corridor to ±12 cm.

Khamis-Roche Age Boundary Validity (Ages 4.0 to 17.5)

Never apply the Khamis-Roche equation to infants under 3 years old. Infantile growth is governed primarily by maternal nutrition and IGF-1/IGF-2 pathways rather than growth hormone and sex steroids. Between birth and 24 months, children commonly cross percentile channels (catch-up or catch-down growth) to find their genetic channel.

Epiphyseal Growth Plate Ossification Signaling the End of Growth

Long bone longitudinal growth ceases entirely once the chondrocytes in the epiphyseal plates (physis) are exhausted and calcify into the epiphyseal line under the influence of circulating estradiol. In girls, this occurs 1.5 to 2.5 years after menarche (average age 14.5-15.5); in boys, growth typically ceases between ages 16.5 and 18.0.

Common Gotchas & Troubleshooting

⚠️Child's Predicted Adult Height is Substantially Shorter Than Both Biological Parents

Verify whether the child has experienced recent chronic illness, untreated celiac disease, severe systemic allergies, or prolonged pediatric stress, all of which suppress the pituitary GH/IGF-1 axis. If the child's height curve drops across more than two major percentile lines (e.g. 75th to 25th), consult a pediatric endocrinologist for a bone-age radiograph and hormonal panel.

⚠️Khamis-Roche Prediction Diverges Dramatically from the Mid-Parental Tanner Height

This divergence occurs when a child's current phenotypic percentile does not match their parents' genetic percentiles. If parents are at the 85th percentile but the child is tracking at the 25th percentile, examine whether a constitutional delay of growth (CDGP) is present, or whether non-genetic factors like sleep architecture, competitive athletic overtraining, or nutritional caloric deficits are suppressing growth velocity.

⚠️Extreme Swings in Predicted Height When Entering Imperial Height in Inches

Quantization error occurs when rounding height to the nearest whole inch (1 inch = 2.54 cm, which represents an entire half-year of normal prepubertal growth). Always measure and enter child height with 0.25-inch (or 0.5-centimeter) precision to avoid false multi-inch trajectory swings.

⚠️Child Was Born Prematurely (<37 Weeks Gestation) Distorting Early Percentile Outputs

For children under 3 years of age born prematurely, calculate chronological age adjusted for gestational prematurity (Chronological Age minus Weeks of Prematurity). Failing to adjust causes premature infants to appear pathologically stunted on standard CDC/WHO charts when their post-conceptual velocity is entirely normal.

Frequently Asked Questions

How accurate is the Khamis-Roche child height predictor compared to bone age X-rays?▼

The Khamis-Roche method has a clinical margin of error within ±2.1 cm (0.83 in) for boys and ±1.7 cm (0.67 in) for girls across 90% of non-syndromic pediatric cases between ages 4 and 17. While invasive left-wrist radiographs using the Greulich-Pyle or Tanner-Whitehouse (TW3) methods provide exact skeletal bone-age ossification, Khamis-Roche achieves 92% of the accuracy of bone-age X-rays without exposing the child to ionizing radiation.

What is the exact formula for calculating a child's adult height from parent heights?▼

The Mid-Parental Target Stature (Tanner method) formula is: for a boy, add the father's height and mother's height, add 13 cm (or 5.12 inches), and divide the sum by 2; for a girl, add the father's height and mother's height, subtract 13 cm (or 5.12 inches), and divide the sum by 2. The 95% target genetic corridor is the resulting figure ±10 cm (±3.94 inches).

Does doubling a 2-year-old child's height accurately predict their adult height?▼

The 2-year doubling rule provides a rough rule-of-thumb heuristic within ±5 cm (±2 in) for boys measured at exactly 24 months, because male children achieve approximately 50% of their final adult stature by age two. For girls, doubling height at 18 to 20 months is more accurate than at 24 months because female skeletal maturation proceeds at a faster biological pace; doubling a girl's height at 24 months tends to overestimate adult height by 3 to 6 cm.

At what age do boys and girls officially stop growing in height?▼

Girls typically reach their final adult height between ages 14 and 16, usually 18 to 24 months following menarche (onset of menstruation), after which circulating estrogen fuses the long bone growth plates. Boys experience peak height velocity later (average age 13.5 to 14.0) and continue linear growth until epiphyseal plate fusion occurs between ages 16 and 18, with minor vertebral growth rarely continuing until age 20.

What is Constitutional Delay of Growth and Puberty (late bloomers)?▼

Constitutional Delay of Growth and Puberty (CDGP) is a normal, non-pathological developmental variant where a child's biological 'bone age' lags behind their calendar age by 1 to 3 years. These children experience delayed onset of the pubertal growth spurt and appear shorter than peers between ages 11 and 14, but their growth plates remain open longer, allowing them to continue growing into their late teens and achieve normal adult height consistent with their genetic potential.

Can diet, sports, or sleeping habits increase a child's predicted adult height?▼

Disclaimer: This tool is provided strictly for educational and informational purposes only and does not constitute formal financial advice or a binding loan commitment. Please consult a qualified financial advisor before making decisions. While 80% of adult stature is determined by polygenic inheritance, chronic malnutrition, caloric deficiency, or sleep deprivation can prevent a child from reaching their genetic ceiling. Human Growth Hormone (HGH) is secreted in nocturnal pulsatile surges primarily during Slow-Wave Sleep (Stage 3 NREM), making 9 to 11 hours of quality sleep, adequate dietary protein, zinc, and vitamin D essential for optimizing growth velocity.

Related Tools & Utilities

All Tools →