Short title

STOP-BANG Calculator & Sleep Apnea Risk

Calculate your STOP-BANG score for sleep apnea risk with this clinical screening tool. Evaluate OSA probability, neck size cutoffs, and pre-op anesthesia risks.

Presets
Lbl symptom section
Lbl stop subscore:0 / 4
SLbl snoring

Desc snoring

TLbl tiredness

Desc tiredness

OLbl apnea

Desc apnea

PLbl hypertension

Desc hypertension

Lbl biometric section
Lbl bang subscore:1 / 4
Lbl meets criteria
Lbl age under50
45
Lbl height5' 9"
Lbl weight175 lbs
B
Lbl bmi: 25.8 kg/m²

Lbl cutoff35

Lbl0 points
NLbl neck circumference
16.0 in

Lbl cutoff neck men

12.0 inLbl does not meet24.0 in
Lbl cofactors title

Desc cofactors

Lbl ess sleepiness

Desc ess sleepiness

Lbl mallampati

Desc mallampati

Lbl resistant bp

Desc resistant bp

Tab cockpit
0Lbl dial lowLbl dial midLbl dial high8
1/ 8 Lbl points of8
Lbl risk tier
Lbl low risk

1 / 8 Lbl criteria positive

Lbl sensitivity rate99%
Lbl specificity rate12%
Lbl criteria breakdown
SLbl crit snoring
0
TLbl crit tiredness
0
OLbl crit apnea
0
PLbl crit hypertension
0
BLbl crit bmi
0
ALbl crit age
0
NLbl crit neck
0
GLbl crit male

Lbl executive recommendation

Rec low risk

Lbl simulator title

Desc simulator

Lbl target weight loss-15 lbs
Lbl projected bmi:23.6 kg/m²
Lbl target neck reduction-1 in
Lbl projected neck:15.0 in
-0
Lbl adjust sliders hint

Lbl projected score: 1 / 8 (Lbl low risk short)

Lbl current: 1Lbl target: 1
Lbl roc title

Desc roc

Lbl cutoff score prefix2Lbl cutoff score prefix3Lbl cutoff score prefix4Lbl cutoff score prefix5Lbl cutoff score prefix6Lbl cutoff score prefix7Lbl cutoff score prefix8100%50%0%Lbl roc x axisLbl roc y axis
Lbl roc legend sensitivityLbl current position
Stat score1 / 8
Stat risk categoryStat low
Stat mod severe prob~12%
Stat severe prob~5%
Disclaimer medical
Technical Reference & Architecture Guide

STOP-BANG Calculator & Sleep Apnea Risk Guide

Calculate your STOP-BANG score for sleep apnea risk with this clinical screening tool. Evaluate OSA probability, neck size cutoffs, and pre-op anesthesia risks.

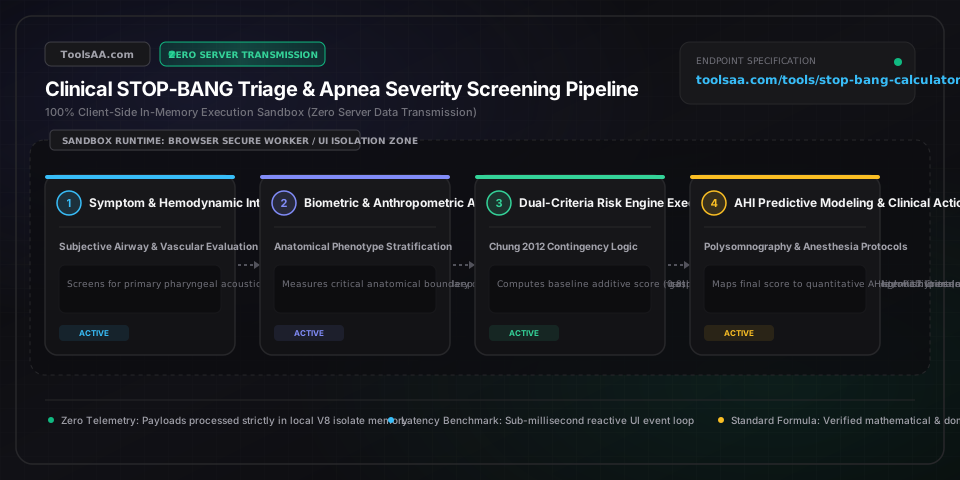
STOP-BANG Calculator & Sleep Apnea Risk Guide — Client-Side In-Memory Architecture & Data Flow

Key Parameters & Controls

Snoring Loudness (S)Subjective Symptom Indicator

Acoustic airway turbulence indicator assessing whether snoring is loud enough to be heard through closed doors or regularly awakens a sleeping partner. Persistent heavy snoring indicates partial pharyngeal collapse and airway resistance.

Default: No (Negative)
Daytime Tiredness / Sleepiness (T)Epworth-Correlated Clinical Indicator

Evaluates unrefreshing sleep, persistent morning brain fog, chronic exhaustion, or unintentionally nodding off during daytime tasks like driving, reading, or watching television, reflecting nocturnal oxygen drops and micro-arousals.

Default: No (Negative)
Witnessed Breathing Pauses / Observed Apnea (O)Observational Diagnostic Indicator

Partner or caregiver confirmation of witnessed breathing pauses, choking sounds, or gasping episodes during sleep. This symptom carries the highest positive predictive value for moderate-to-severe obstructive sleep apnea.

Default: No (Negative)
Systemic Arterial Blood Pressure (P)Cardiovascular Comorbidity Indicator

Clinical confirmation of resting systolic blood pressure of 130 mmHg or higher, diastolic blood pressure of 80 mmHg or higher, or current treatment with antihypertensive medications. Nocturnal oxygen drops repeatedly stimulate the sympathetic nervous system.

Default: No (Negative)
Body Mass Index Threshold (B)Anthropometric Cutoff Indicator

Weight-to-height clinical benchmark set at greater than 35 kg/m2. Elevated adipose deposition in the parapharyngeal fat pads directly compresses the upper airway and increases collapse susceptibility during deep sleep.

Default: No (BMI <= 35 kg/m2)
Chronological Age Threshold (A)Demographic Risk Indicator

Age cutoff benchmarked at older than 50 years. Muscle tone in the pharyngeal dilator muscles and nocturnal compensatory airway reflexes naturally decline as the body matures beyond the fifth decade.

Default: No (Age <= 50)
Cricothyroid Neck Circumference (N)Anatomical Airway Measurement

Standardized collarline measurement taken at the cricothyroid membrane: greater than 17 inches (43 cm) for men, or greater than 16 inches (41 cm) for women. Regional neck circumference correlates more directly with airway crowding than overall body weight.

Default: No (<= 17 in male / <= 16 in female)
Biological Sex Classification (G)Endocrine & Anatomical Classifier

Biological male status adds 1 point due to longer upper airway dimensions, greater upper-body fat distribution, and differences in genioglossus muscle responsiveness compared to premenopausal females.

Default: Female (0 points)
Pro Tips & Best Practices

Always Apply the Chung 2012 Alternative High-Risk Rule to Scores 3 and 4

Standard scoring designates 3 to 4 as 'Intermediate Risk', which often causes individuals to postpone clinical consultations. However, validated research by Chung et al. (2012) demonstrates that if a person scores 3 or 4 with at least 2 positive STOP symptoms AND is either male, has a BMI over 35 kg/m2, or has an enlarged neck circumference (>16 inches for women, >17 inches for men), their true probability of moderate-to-severe OSA exceeds 80%, identical to patients scoring 5 or higher.

Avoid Measuring Neck Circumference Over the Thyroid Cartilage Prominence

Positioning the measuring tape directly across the Adam's apple (thyroid prominence) artificially adds 0.5 to 1.2 inches due to cartilage protrusion. For true clinical precision, position the tape measure just below the laryngeal prominence at the level of the cricothyroid membrane while standing upright with your head in a neutral, forward-looking posture.

Watch for the Female Postmenopausal False-Negative Masking Effect

Women frequently score lower on the classic STOP-BANG screening because sleep-disordered breathing often manifests as morning tension headaches, insomnia, restless legs, mood shifts, and daytime fatigue rather than loud rattling snores. A postmenopausal woman with an intermediate score of 3 warrants clinical evaluation just as proactively as a high-scoring male.

Pre-Operative Opioid and Sedative Caution in High Scorers

For individuals scheduled for outpatient or elective surgery, scoring 5 or higher (or meeting the Alternative High-Risk criteria) substantially raises the risk of post-extubation airway narrowing when exposed to general anesthesia, narcotics, or muscle relaxants. Always share your STOP-BANG score with your surgical team so they can arrange tailored respiratory monitoring and gentle recovery positioning.

Common Gotchas & Troubleshooting

⚠️Unsure if you snore or stop breathing because you sleep alone without a bed partner

When sleeping solo, the 'S' (Snoring) and 'O' (Observed pauses) questions cannot be definitively confirmed by another person. Look for secondary acoustic clues such as waking up gasping, having a persistent dry mouth or sore throat every morning, or use a validated sleep-sound audio recording app for two consecutive nights to review respiratory noise.

⚠️Athletic and muscular individuals trigger the BMI > 35 cutoff without excess body fat

Powerlifters, crossfitters, and heavy athletes often cross the 35 kg/m2 BMI threshold due to dense skeletal muscle mass rather than adiposity. In these cases, place primary diagnostic weight on cricothyroid neck circumference and daytime alertness symptoms. Even without obesity, hyper-developed neck musculature can place external mechanical weight on the airway during deep muscle relaxation.

⚠️Total score is only 3, but you experience severe daytime fatigue and unrefreshing sleep

First check your STOP component score: if daytime sleepiness is accompanied by observed choking or snoring (STOP >= 2) in a male patient, immediately apply the Chung 2012 reclassification to High Risk. If you do not meet that criterion, consult a sleep physician to evaluate non-apnea sleep disruptions such as upper airway resistance syndrome (UARS), iron deficiency, or circadian phase disorders.

Frequently Asked Questions

How is the STOP-BANG score calculated and what are the risk cutoffs?▼

The STOP-BANG score is calculated by giving 1 point for every 'Yes' across 8 questions: Snoring loudly, Tiredness during the day, Observed breathing pauses, high blood Pressure, BMI over 35 kg/m2, Age over 50 years, Neck circumference over 16 inches (women) or 17 inches (men), and biological Male sex. Total scores range from 0 to 8: Low Risk is 0 to 2, Intermediate Risk is 3 to 4, and High Risk is 5 to 8. A score of 3 or 4 is also upgraded to High Risk if the patient has 2 or more STOP symptoms combined with male sex, BMI > 35, or high neck circumference.

What is the accuracy of the STOP-BANG questionnaire compared to polysomnography?▼

At a standard cutoff of score >= 3, STOP-BANG demonstrates an extraordinary sensitivity exceeding 93% for moderate sleep apnea (Apnea-Hypopnea Index >= 15) and nearly 100% for severe sleep apnea (AHI >= 30), meaning it virtually never misses severe cases. While its specificity at score 3 is modest (around 30% to 40%), patients scoring 5 or higher reach a specificity over 80% to 85%, confirming a very high probability of true obstructive sleep apnea on overnight polysomnography.

What is the difference between the STOP questionnaire and the STOP-BANG questionnaire?▼

The original STOP questionnaire developed in 2008 contains only the 4 subjective lifestyle questions: Snoring, Tiredness, Observed breathing pauses, and high blood Pressure (scored 0 to 4). The expanded STOP-BANG questionnaire adds 4 objective anatomical and demographic measurements: BMI > 35 kg/m2, Age > 50, Neck circumference, and biological Gender. Incorporating BANG significantly improves clinical accuracy, raising the statistical receiver operating characteristic (ROC) curve from 0.70 to over 0.82.

Can you have severe obstructive sleep apnea with a low STOP-BANG score of 0, 1, or 2?▼

Yes, although it is statistically uncommon because the negative predictive value for severe apnea at scores 0 to 2 exceeds 95%. False negatives can occur in premenopausal women, slender individuals with structural craniofacial retrognathia (a recessed lower jaw), enlarged tonsils, or isolated REM-dependent sleep apnea. Clinical evaluation and a diagnostic sleep study always take precedence over questionnaire screening if noticeable symptoms persist.

Why does neck circumference matter more than body weight in sleep apnea screening?▼

Disclaimer: This tool is provided strictly for educational and informational purposes only and does not constitute formal financial advice or a binding loan commitment. Please consult a qualified financial advisor before making decisions. Neck circumference directly reflects regional soft tissue crowding around the throat where airway collapse occurs. While total weight or BMI measures generalized mass, cervical fat deposits and thickened pharyngeal walls exert direct mechanical pressure against the collapsible lateral airway. When muscle tone naturally drops during deep and REM sleep, an enlarged neck (>16 inches in females, >17 inches in males) creates higher closing pressures that obstruct airflow.

Related Tools & Utilities

All Tools →